The Legislation Package
war-on-disease, 1-percent-treaty, medical-research, public-health, peace-dividend, decentralized-trials, dfda, dih, victory-bonds, health-economics, cost-benefit-analysis, clinical-trials, drug-development, regulatory-reform, military-spending, peace-economics, decentralized-governance, wishocracy, blockchain-governance, impact-investing
Here’s how democracy actually works: Lobbyists write bills and give them to politicians who can’t read. Those politicians vote based on who donated most to their campaign. This chapter is five bills, pre-written, ready to hand to whichever politician you can afford. You’re about to become the best lobbyist in history, except your bills actually help people instead of killing them.
Each bill is designed to pass because it gives politicians what they crave: money, votes, and the ability to claim they did something.
The Treaty Implementation Act: Making It Real
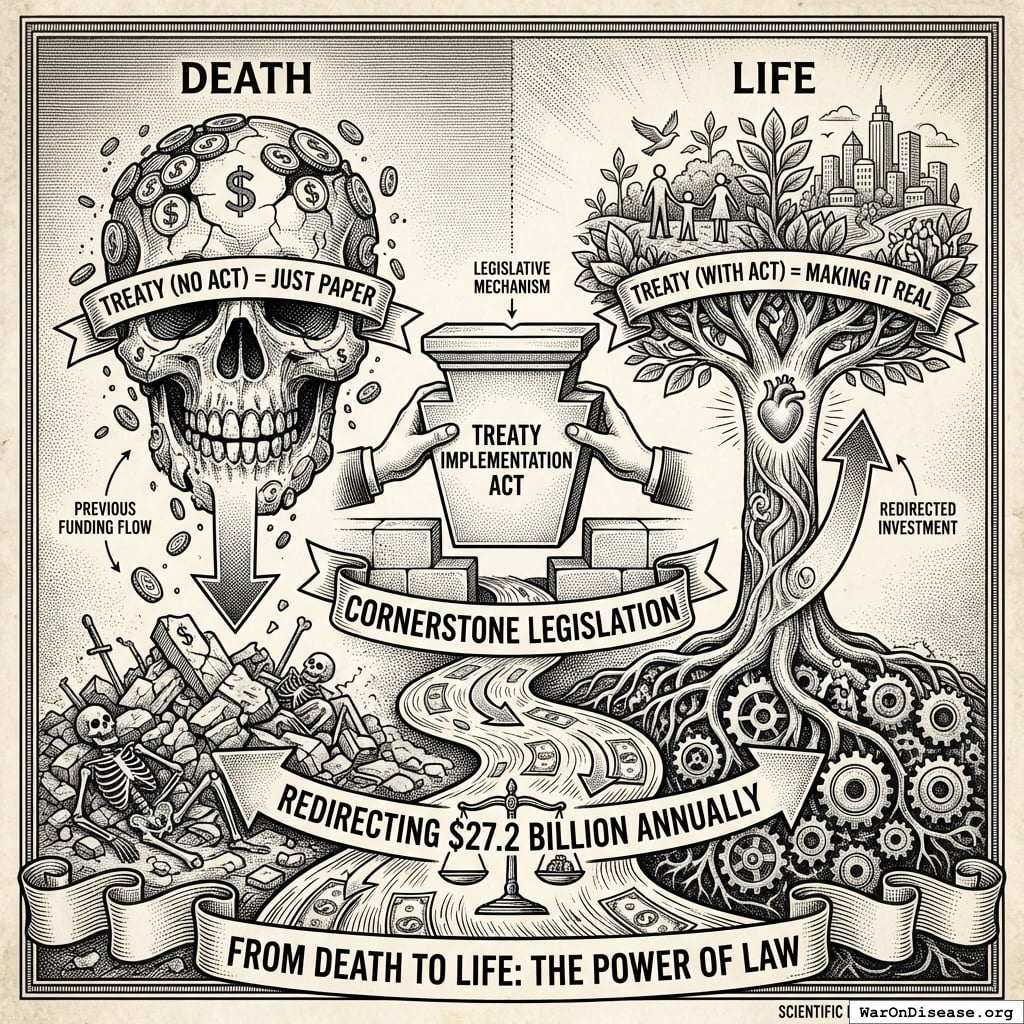
This is your cornerstone legislation. Without it, the treaty is just paper. With it, you redirect $27.2 billion annually from death to life.
The Core Provisions
Section 1: Authorization
“The United States shall implement the 1% Treaty1 2 upon ratification by 3+ nations”
“1% of the United States military budget (currently ~$10 billion) shall be automatically redirected to a 1% Treaty Fund as the nation’s contribution to the treaty fund.”
“Funds transfer via auditable automated treasury rules on first day of fiscal year”
No annual appropriation needed (politicians can’t kill it later)
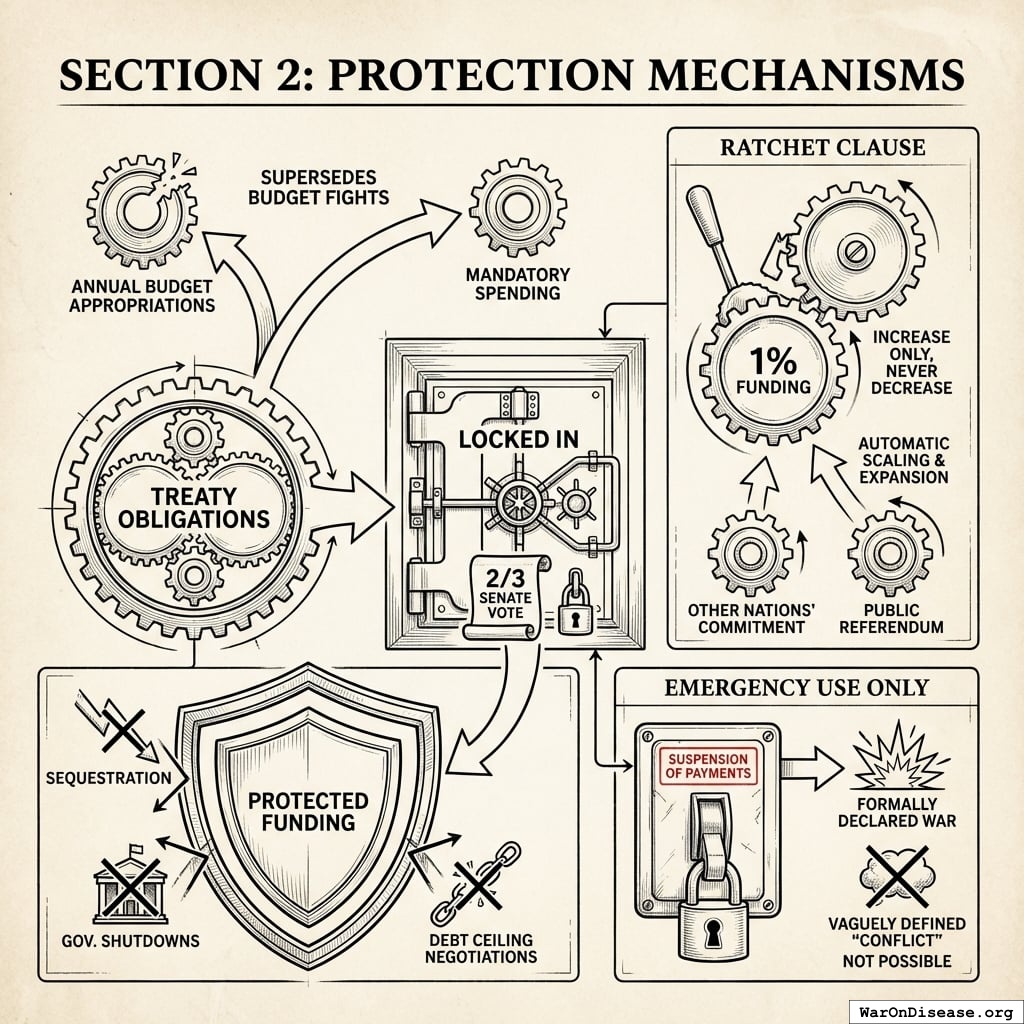
Section 2: Protection Mechanisms
- Supersedes Budget Fights: Treats treaty obligations as mandatory spending. Supersedes annual budget appropriations.
- Locked In: Withdrawal from the treaty requires a very difficult 2/3 Senate vote.
- Protected Funding: Funds are exempt from sequestration, government shutdowns, and debt ceiling negotiations.
- Ratchet Clause: The 1% funding can only increase, never decrease. It automatically scales if other nations increase their commitment. Public referendum can expand it further.
- Emergency Use Only: Only a formally declared war can suspend payments. A vaguely defined “conflict” does not qualify.
Avoiding Common Treaty Failure Modes
Treaties fail in predictable ways. They all fail for the same boring reasons. Here’s how this one avoids the common killers:
Reservation Games. Countries love to sign treaties then add exceptions that gut them. It’s like joining a gym but reserving the right to never go. Solution: no reservations permitted. All or nothing. Take it or leave it.
Ratification Delays. Sign with fanfare, take a photo, then let it die in committee forever. Your species calls this “diplomacy.” Solution: provisional application. Takes effect on signature. Ratification just formalizes what already started.
Creative Accounting. Reclassify “military” spending as “peacekeeping” or “homeland security” to dodge obligations. This is beige crime: making theft so procedurally dull that nobody investigates. Reclassifying “military” as “peacekeeping” is the bureaucratic equivalent of stealing someone’s car by renaming it “shared mobility infrastructure.” Solution: compliance verified by public ledger and independent audits. Relabeling a submarine as “humanitarian infrastructure” will be noticed, because $27.2 billion leaves a paper trail that 193 countries, every bondholder with a Bloomberg terminal, and one moderately competent auditor can follow.
Parliamentary Obstacles. Executive signs, legislature refuses to implement. Solution: the treaty sets the percentage; Congress implements it through the annual National Defense Authorization Act (NDAA), the same way NATO’s spending commitments work. After Medellin v. Texas (2008), your Supreme Court said not all treaties are self-executing, so this one doesn’t try to bypass Congress. It just gives Congress a job to do. The Incentive Alignment Bond mechanism makes sure they actually do it (by making “forgetting” expensive).
Section 3: The Candy for Congress

- Each state gets proportional pragmatic clinical trial funding
- Naming rights for politicians: “The Senator Smith Cancer Center”
- Job creation metrics published quarterly (re-election fuel)
- Local preference for trial sites (pork barrel paradise)
Why Politicians Will Vote Yes
Your politicians operate in two tribes. One tribe wraps everything in a flag; the other wraps everything in a heart. Same bill, different wrapping paper. The flag tribe hears “cuts waste, supports troops, America leads.” The heart tribe hears “healthcare access, reduces inequality, historic expansion.” Both tribes hear “your constituents stop dying and start voting for you.” The wrapping doesn’t matter. The incentive does.

The Incentive Alignment Bond mechanism funds independent political support for every politician who votes yes. Opposition faces primary challenges. Cured constituents vote. History books write about them positively. All four things politicians actually care about, delivered simultaneously.
The Legislative Hack
Bundle it with military funding. Politicians rarely vote against military bills (career suicide). Your treaty implementation becomes a tiny rider on a massive bill they have to pass.
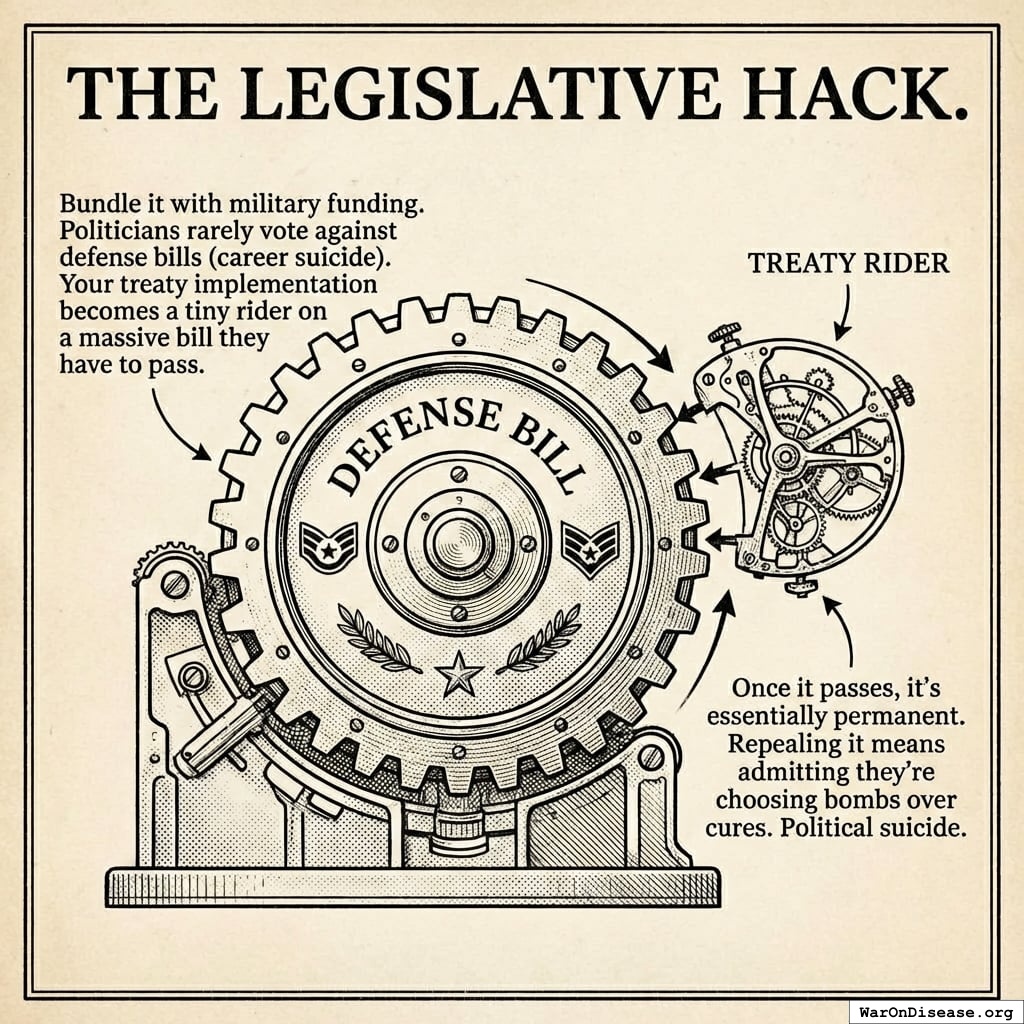
Once it passes, it’s essentially permanent. Repealing it means admitting they’re choosing bombs over cures. Political suicide.
The Authorization Act for your Decentralized Institutes of Health: Creating Your Machine
This creates your Decentralized Institutes of Health (DIH). The machine that converts bomb money into trial slots.

The Structure Designed to Resist Capture
Section 1: Establishment
- “A Decentralized Institutes of Health (DIH) network is created as an independent agency” (not under HHS control)
- “Governed by transparent rules and auditable automation” (not by political appointees)
- “Funded by treaty obligations” (no appropriations needed)
- “Exempt from government hiring rules” (can actually pay competitive salaries)
Section 2: Powers
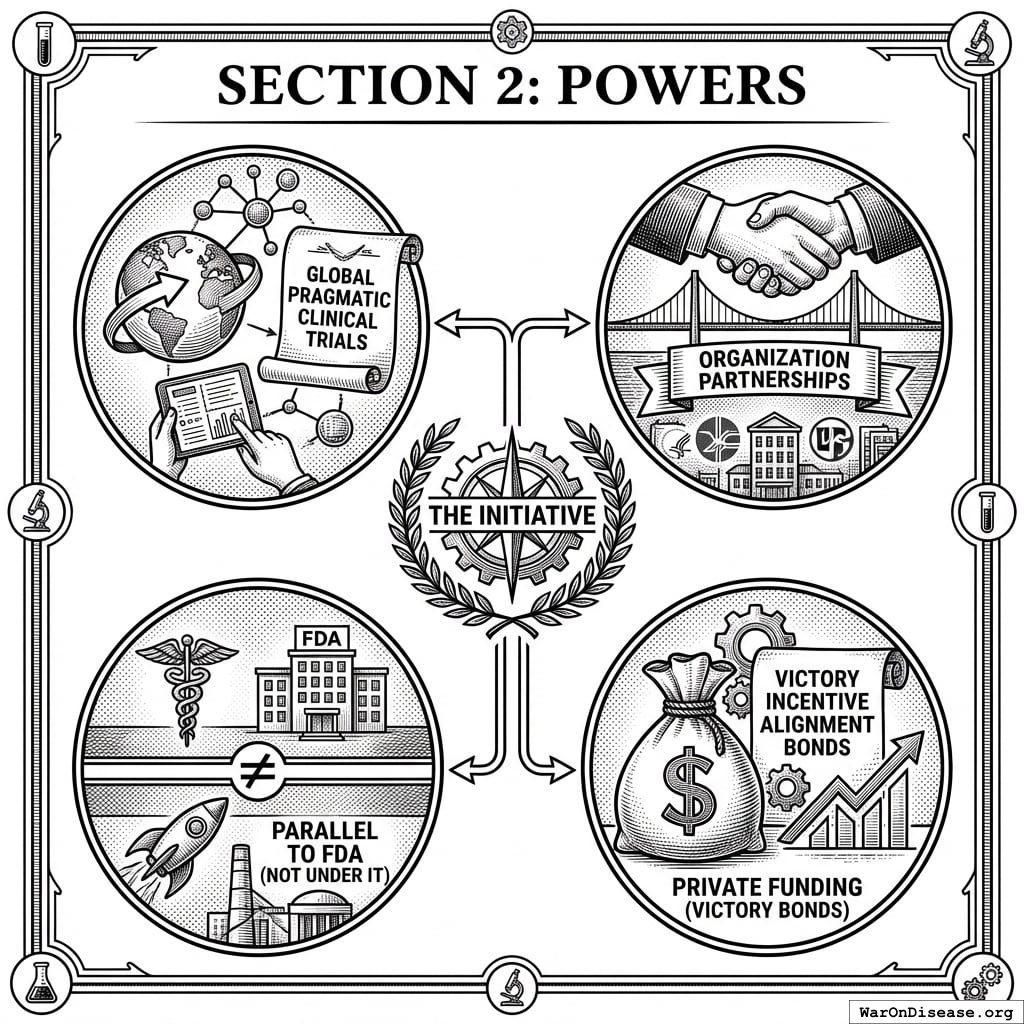
- Can launch and manage any pragmatic clinical trials globally
- Can partner with any organization
- Can operate parallel to FDA (not under it)
- Can accept private funding (VICTORY Incentive Alignment Bonds3)
Section 3: Governance
- No board of directors (can’t be captured)
- Collective-choice decisions via Wishocracy4 voting
- Transparent public-ledger operations (radical transparency)
- Annual public audits (trust through verification)
The Trojan Horse Approach
Frame it as a “pilot program” or “innovation testbed.” Politicians love pilots because they sound temporary and innovative. Don’t mention that successful pilots never get cancelled.
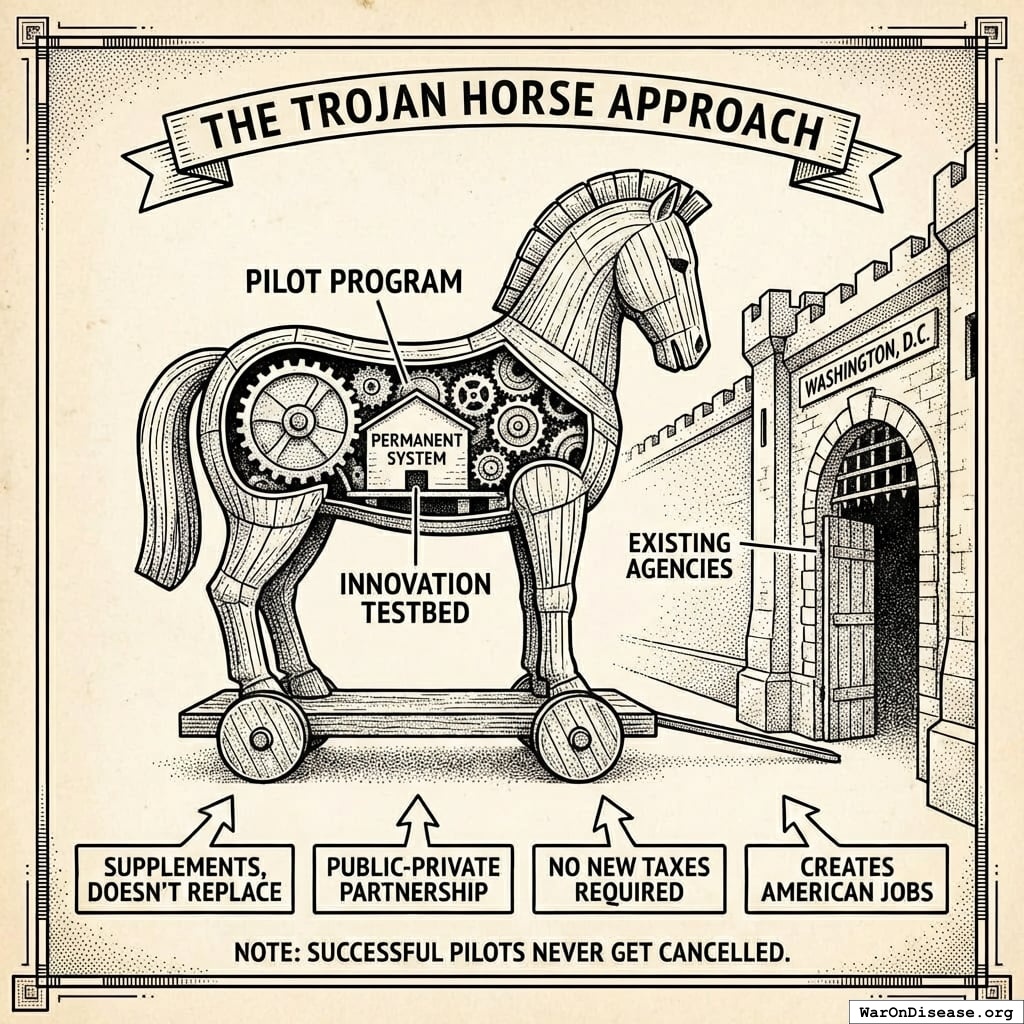
Your politicians will approve the pilot because it sounds temporary. Nothing temporary has ever been cancelled on your planet. You have 47 “temporary” government programs from the 1930s still running. The pilot is a permanent program wearing a lab coat.
The Poison Pills for Opposition
Insert provisions that make opposition toxic:
- Public salary database (shows who’s blocking cures)
- Mandatory disclosure of pharma donations
- Real-time voting records on health issues
- Patient testimony requirements (let dying kids speak)
Opposition means explaining why you’re against transparency and dying children. Good luck with that.

The Parallel Track Act: Your Regulatory Revolution
This act creates your decentralized FDA5,6. It builds a legal pathway for treatments to operate outside the FDA’s 17-year death march. Patients get choices. Researchers get freedom. People stop dying while waiting for approval.
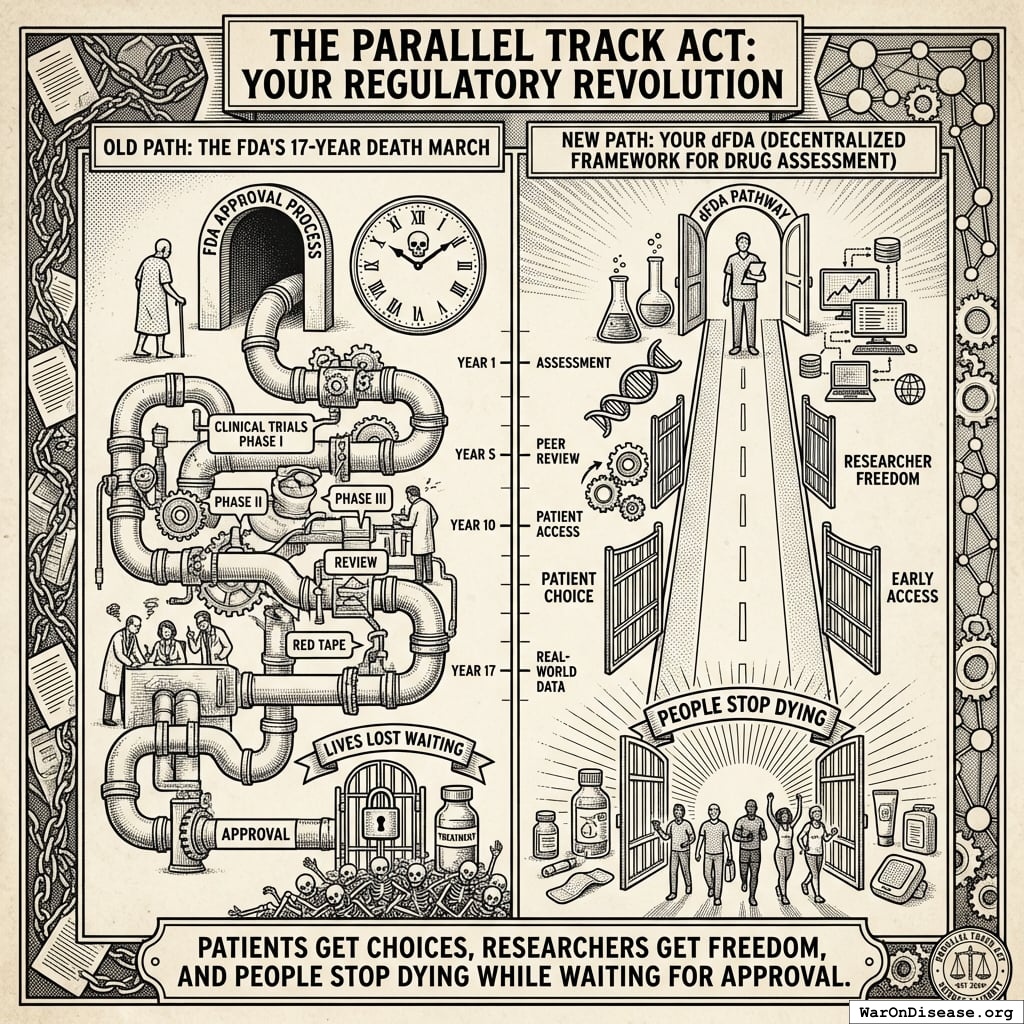
The Legal Architecture
Section 1: The Parallel Pathway
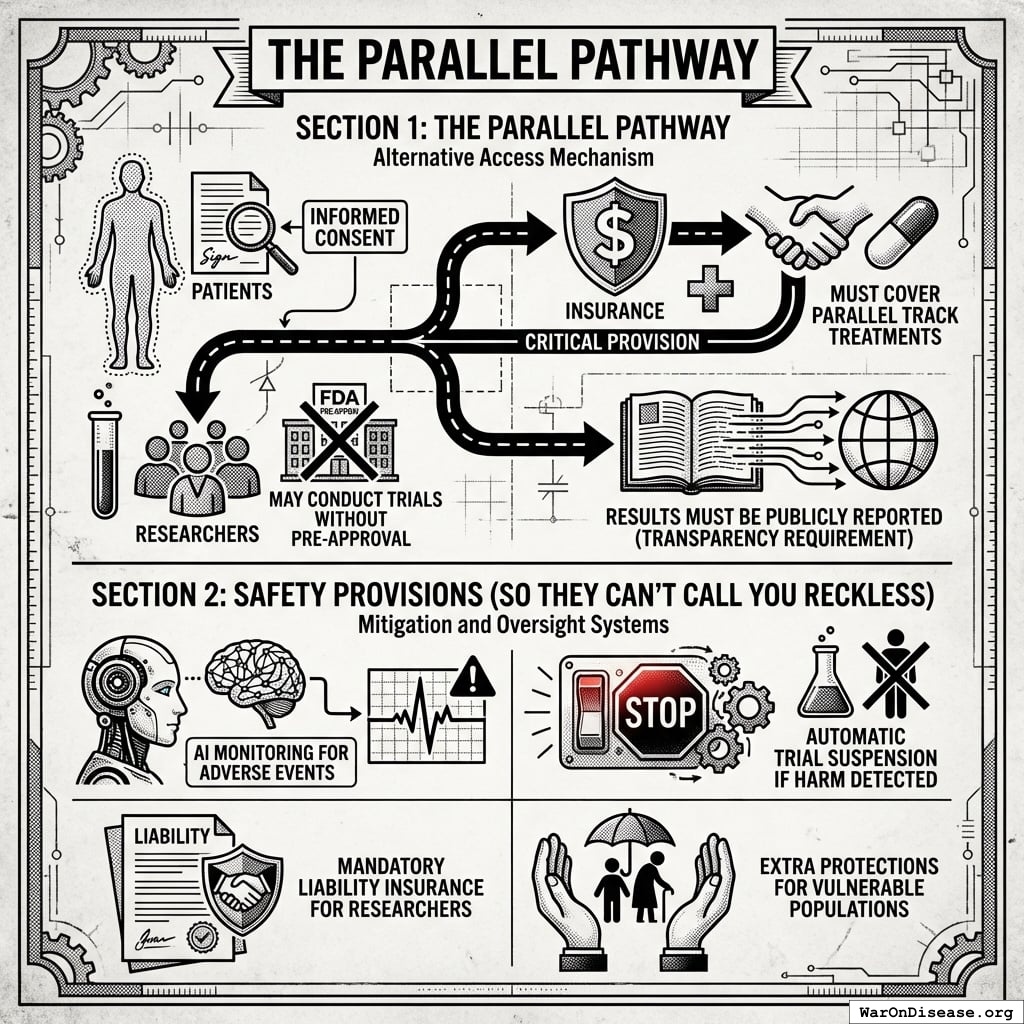
- “Patients may access treatments in active trials with informed consent”
- “Researchers may conduct trials without FDA pre-approval”
- “Insurance must cover parallel track treatments” (critical provision)
- “Results must be publicly reported” (transparency requirement)
Section 2: Safety Provisions (So They Can’t Call You Reckless)
- AI monitoring for adverse events
- Automatic trial suspension if harm detected
- Mandatory liability insurance for researchers
- Extra protections for vulnerable populations
Section 3: The Data Revolution
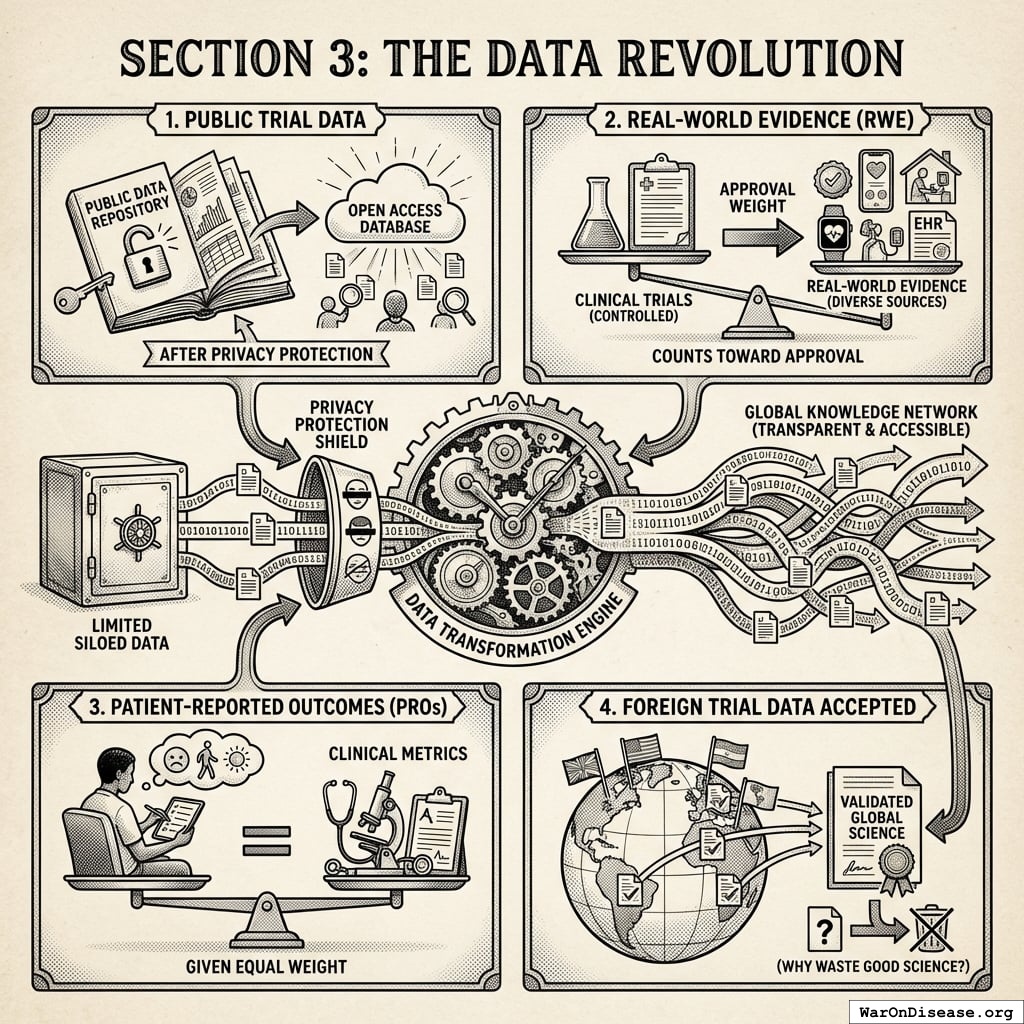
- All trial data becomes public (after privacy protection)
- Real-world evidence counts toward approval
- Patient-reported outcomes given equal weight
- Foreign trial data accepted (why waste good science?)
Why Politicians Will Vote Yes (They Have No Choice)
Politicians are terrified of being blamed for the next thalidomide. They are not terrified of being blamed for the 150,000 who die daily from untested treatments. Your species fears the wrong risk by a factor of 3,389 (90% CI: 1,811-5,734). The pitch is simple: more data makes things safer, not less. Monitoring a million patients in real time catches problems faster than testing a thousand patients for a decade.
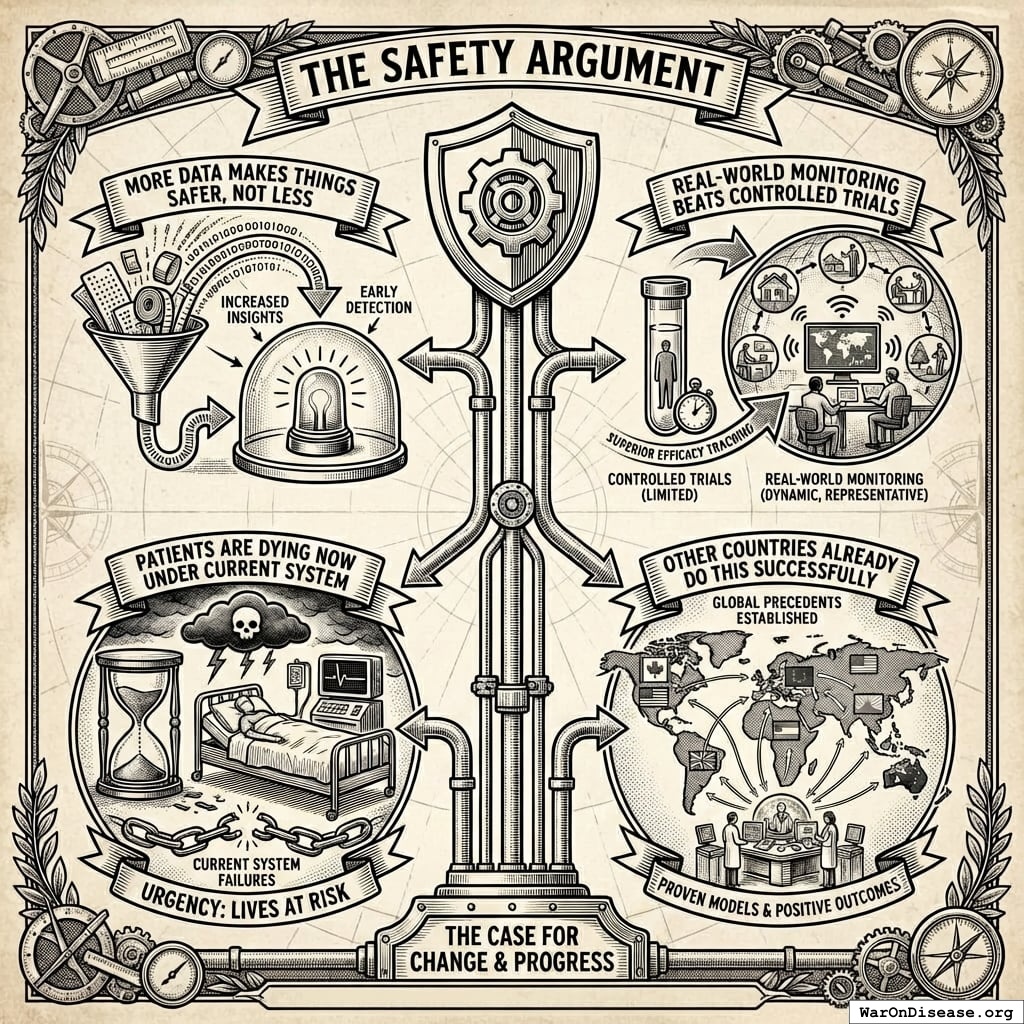
Your politicians come in two flavors. One flavor says “freedom” and the other says “access.” They mean the same thing but in different fonts. Both flavors vote yes on letting dying people try medicine, because the alternative is explaining on television why bureaucrats should decide who lives.
The Implementation Trick
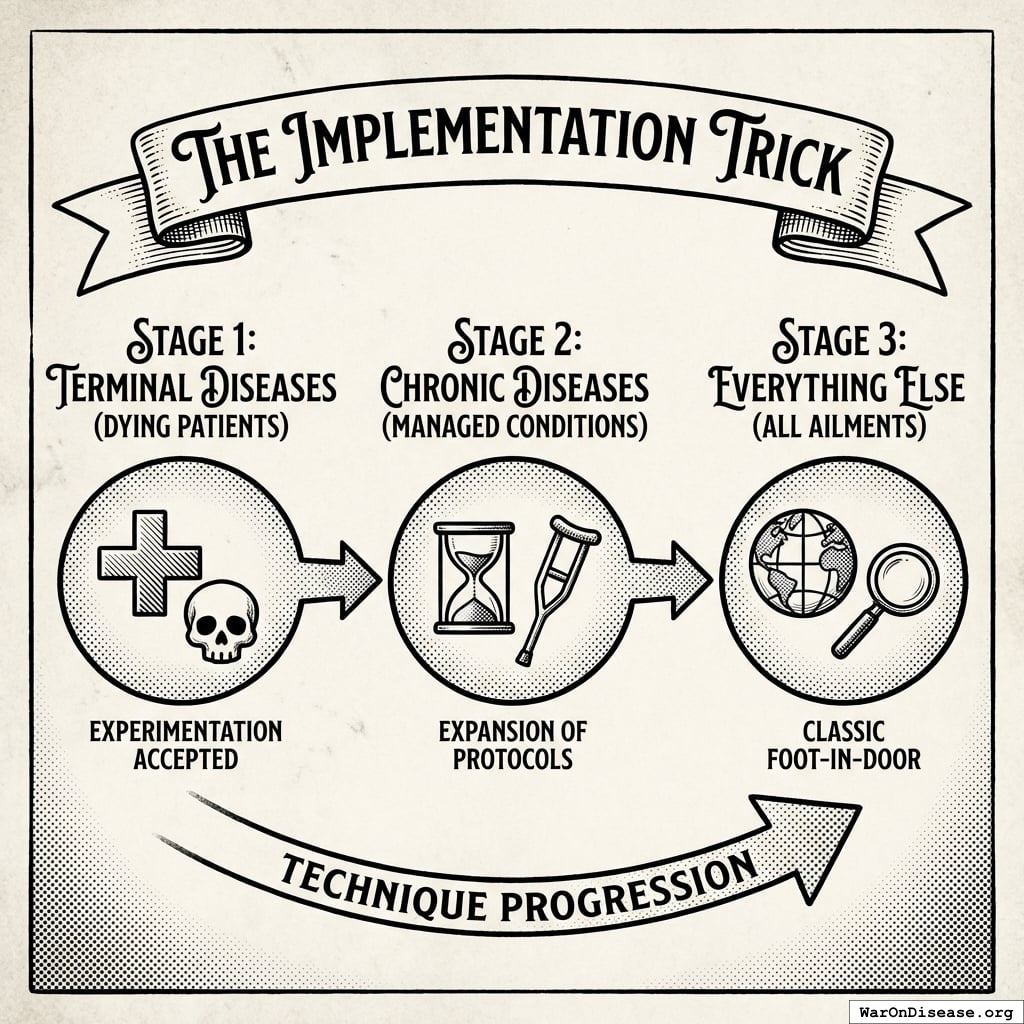
Start with terminal diseases only. Nobody argues against letting dying people try treatments. Once it works, expand to chronic diseases. Then everything else. Classic foot-in-door technique.
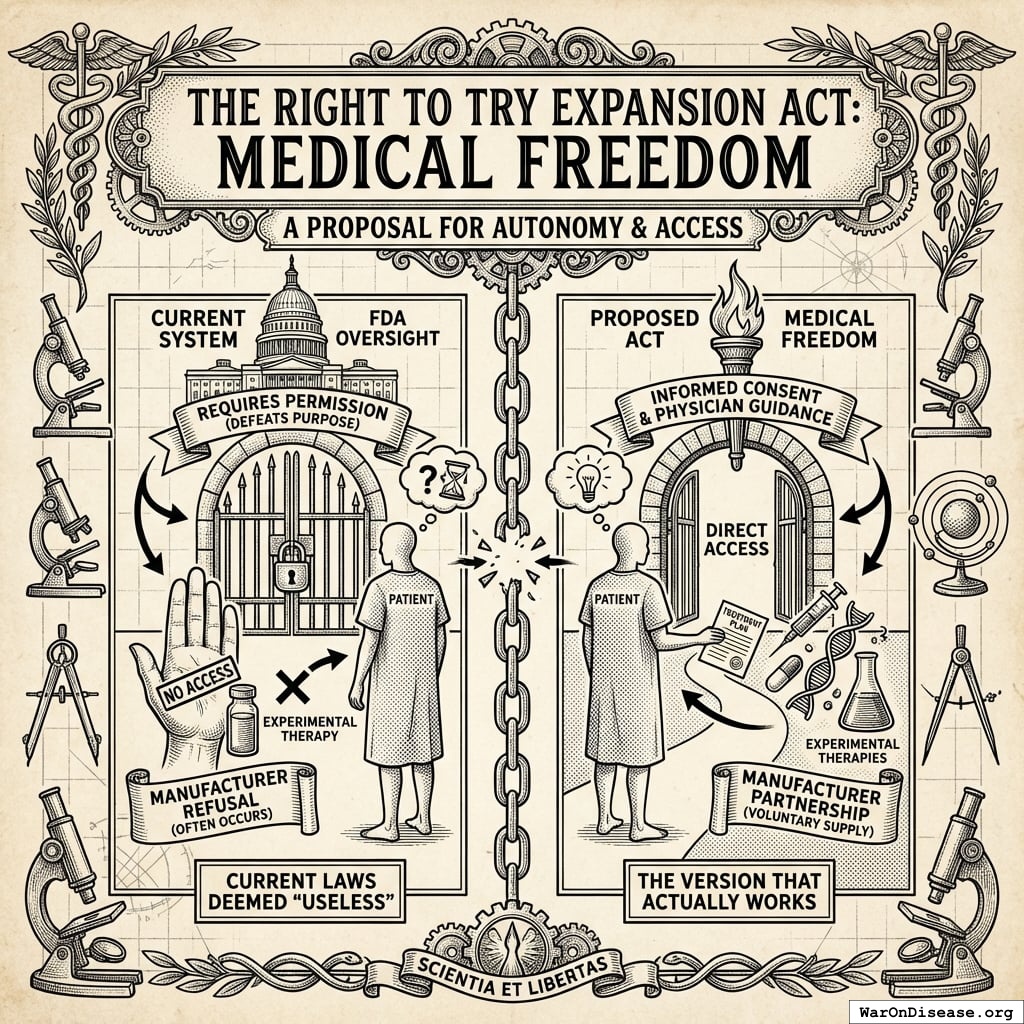
The Right to Try Expansion Act: Medical Freedom
Current Right to Try laws are useless. They require FDA permission (defeats the purpose) and manufacturers can refuse (they often do). Here’s the version that actually works.
The Provisions That Matter
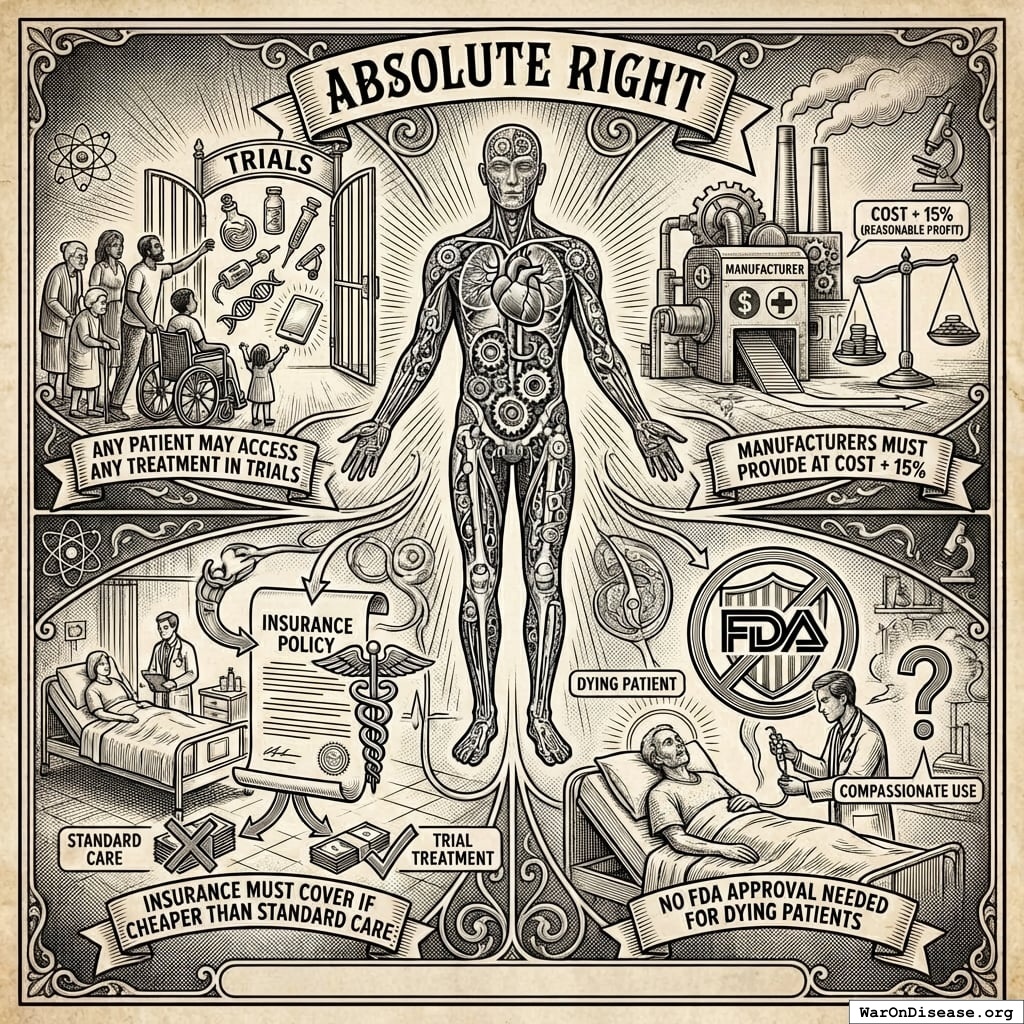
Section 1: Absolute Right
- “Any patient may access any treatment in trials”
- “Manufacturers must provide at cost + 15%” (reasonable profit)
- “Insurance must cover if cheaper than standard care”
- “No FDA approval needed for dying patients”
Section 2: The Subsidy System
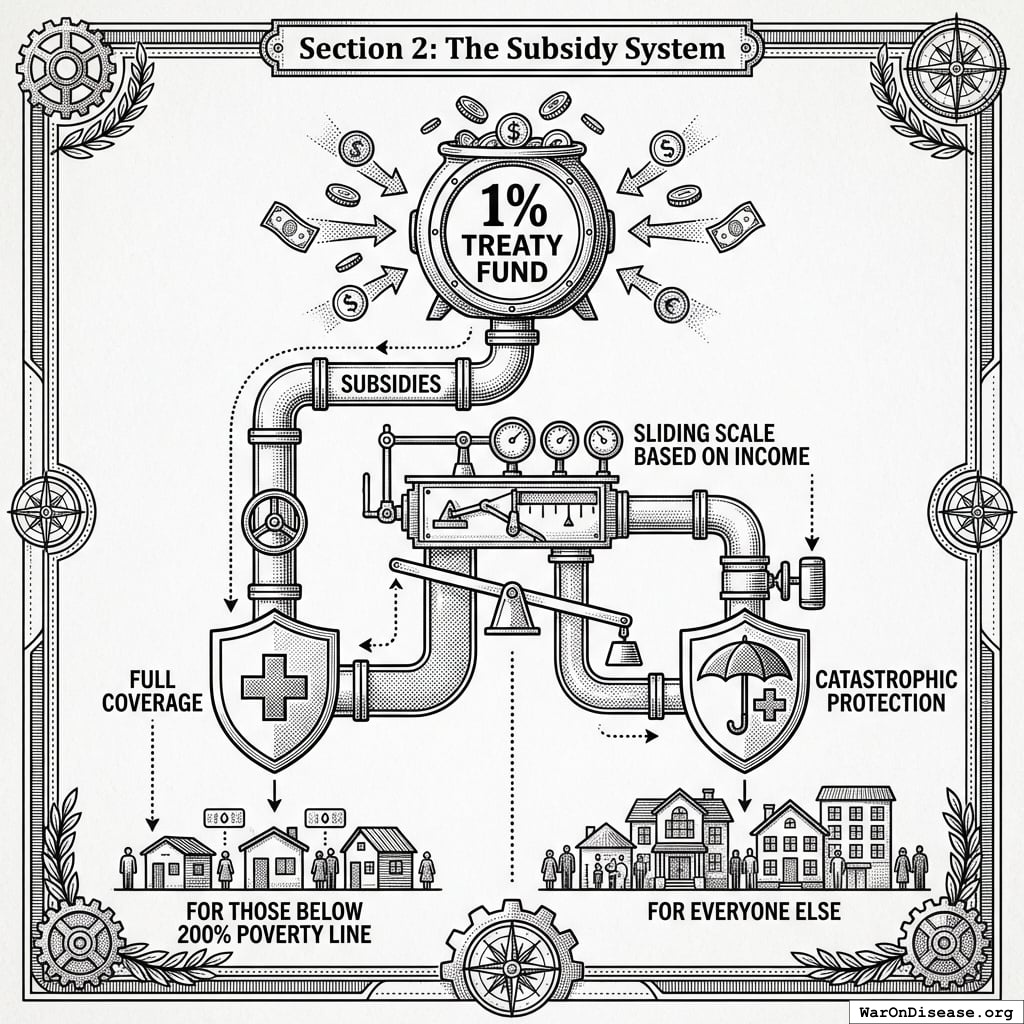
- Subsidies from a 1% Treaty Fund make treatments affordable
- Sliding scale based on income
- Full coverage for those below 200% poverty line
- Catastrophic protection for everyone else
Section 3: The Data Exchange
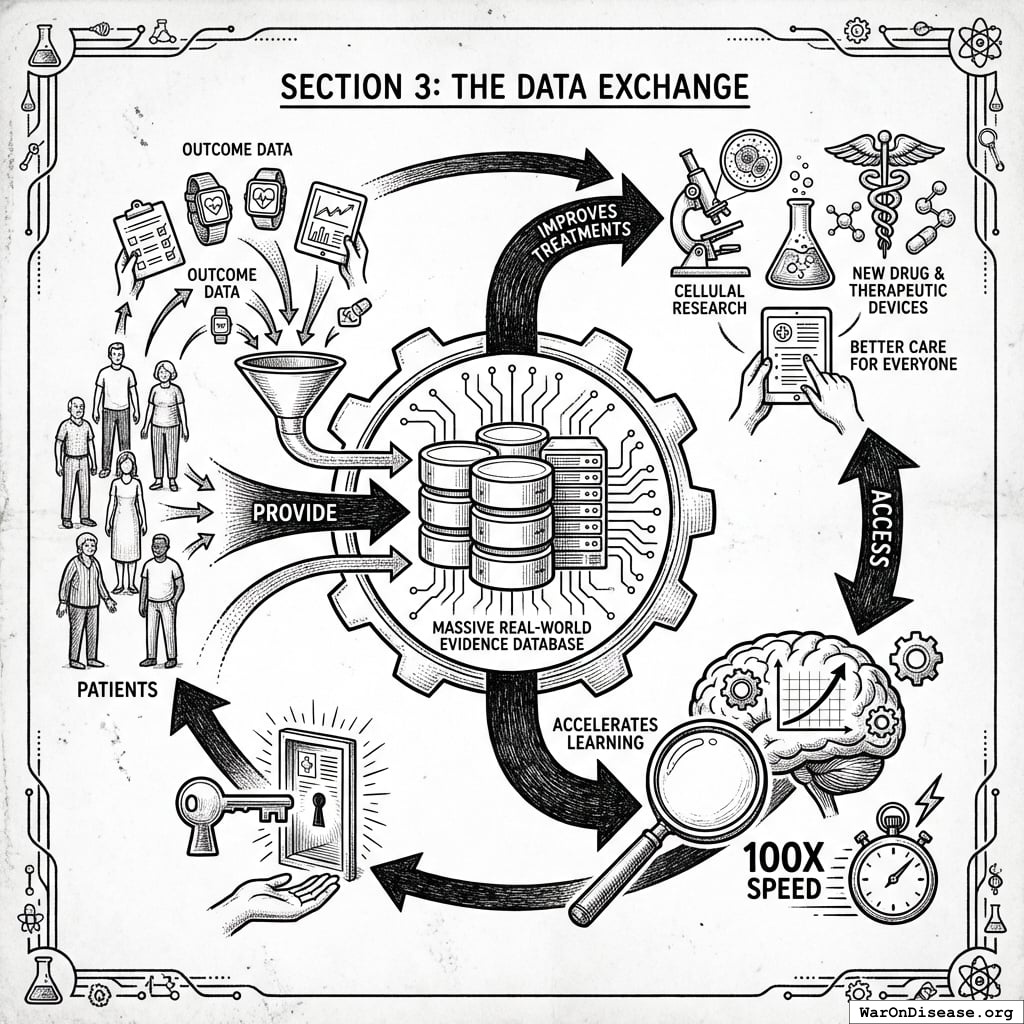
- Patients provide outcome data in exchange for access
- Data improves treatments for everyone
- Creates massive real-world evidence database
- Accelerates learning by 100X
The Emotional Blackmail Strategy
Politicians already parade dying children at press conferences. You are just changing the script. The new line is one question: “Why won’t you let me try to live?”
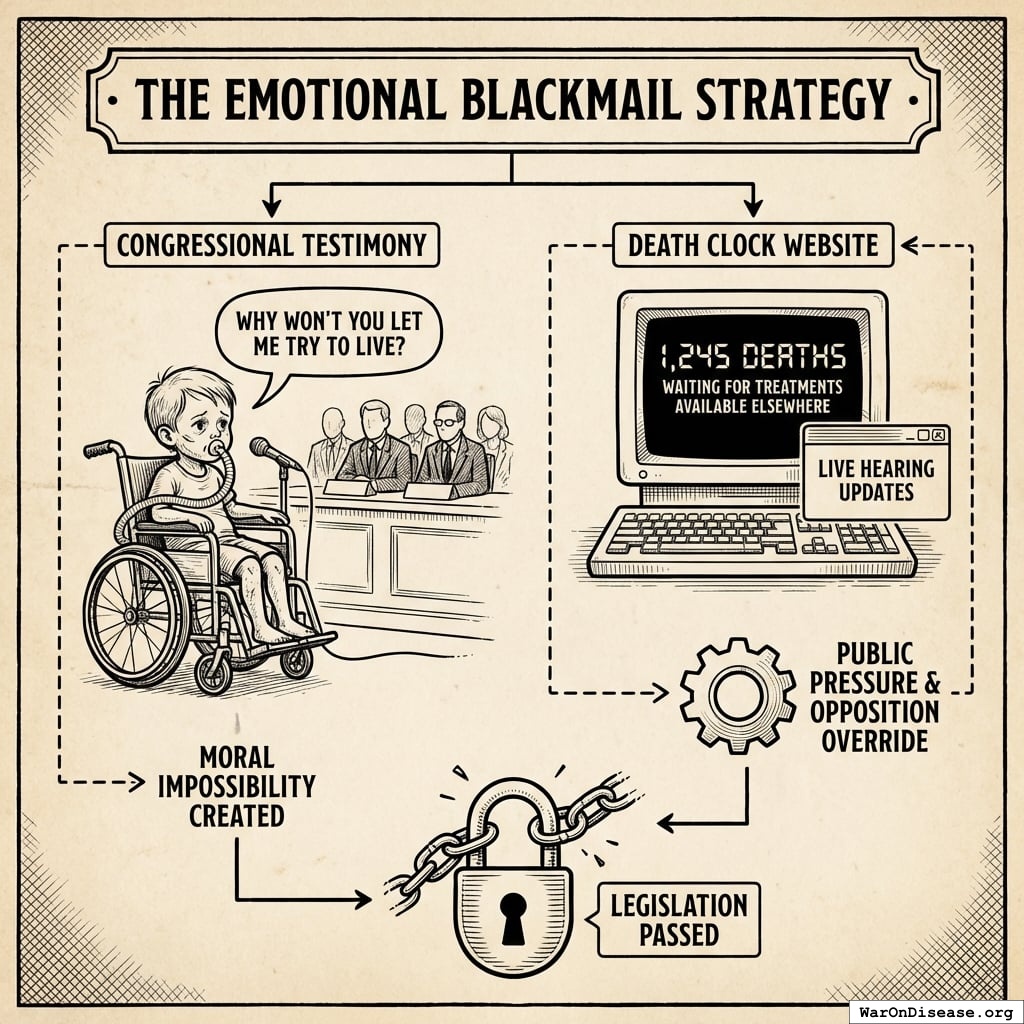
Create a “Death Clock” website. Show people dying while waiting for treatments available elsewhere. Update it live during hearings. Make opposition morally impossible.
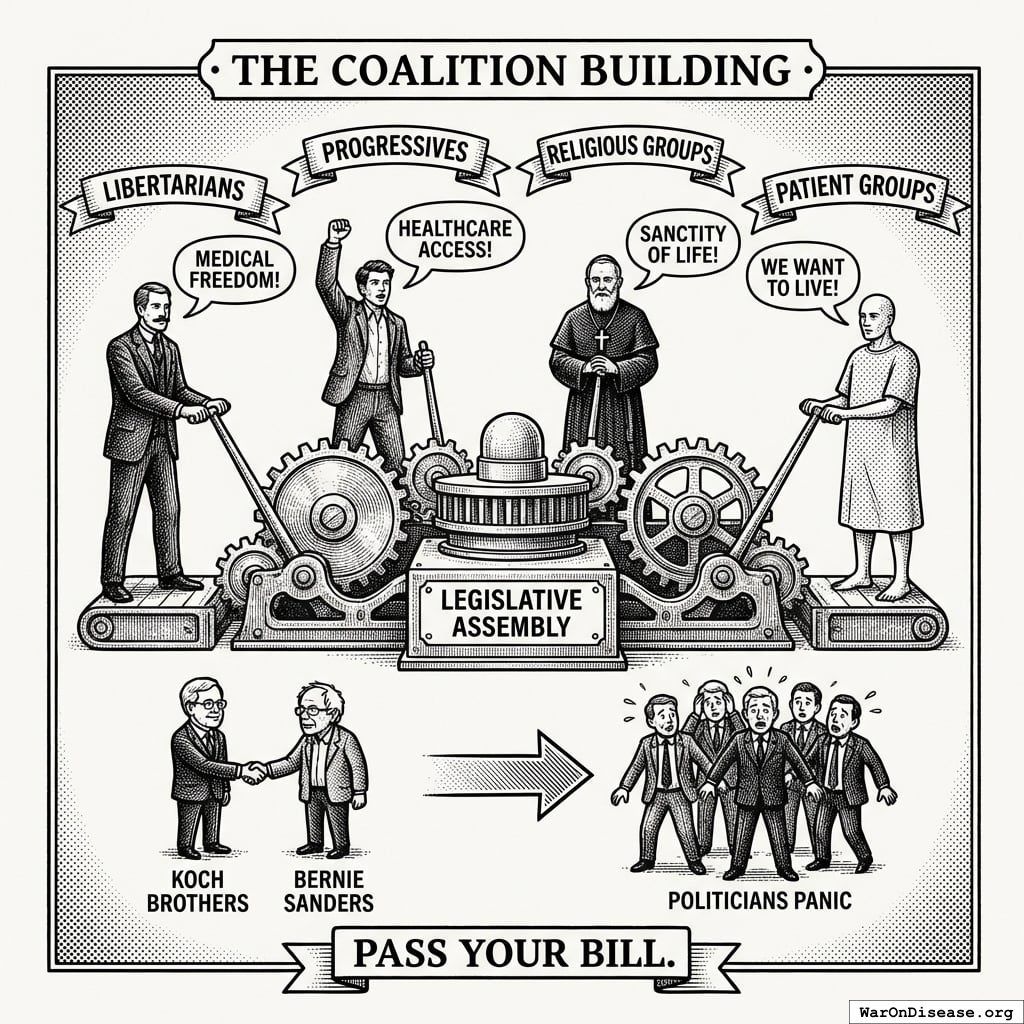
Your species has libertarians, progressives, religious groups, and patient groups. They agree on almost nothing. They all agree dying is bad. When the Koch Brothers and Bernie Sanders agree, politicians panic and pass your bill. This is the only bipartisan coalition in human history that required zero compromise, because “not dying” is not a partisan position. It just looks like one because nobody proposed it.
The Budget Reallocation Act: Moving the Money
This is the technical bill that actually moves the money. Boring but critical. Without it, everything else is theater.
The Money Flow Mechanics
Section 1: Automatic Transfer
- 1% of DoD budget transferred on October 1st annually
- Via Federal Reserve direct transfer into the treaty fund’s designated treasury rails
- To a 1% Treaty Fund account structure governed by transparent, hard-to-rewrite rules
- Cannot be rescinded or redirected without treaty withdrawal
Section 2: The Protection Clauses
- Funds exempt from sequestration
- Exempt from government shutdown
- Exempt from debt ceiling fights
- Treated as treaty obligation, not appropriation
Section 3: The Growth Mechanism
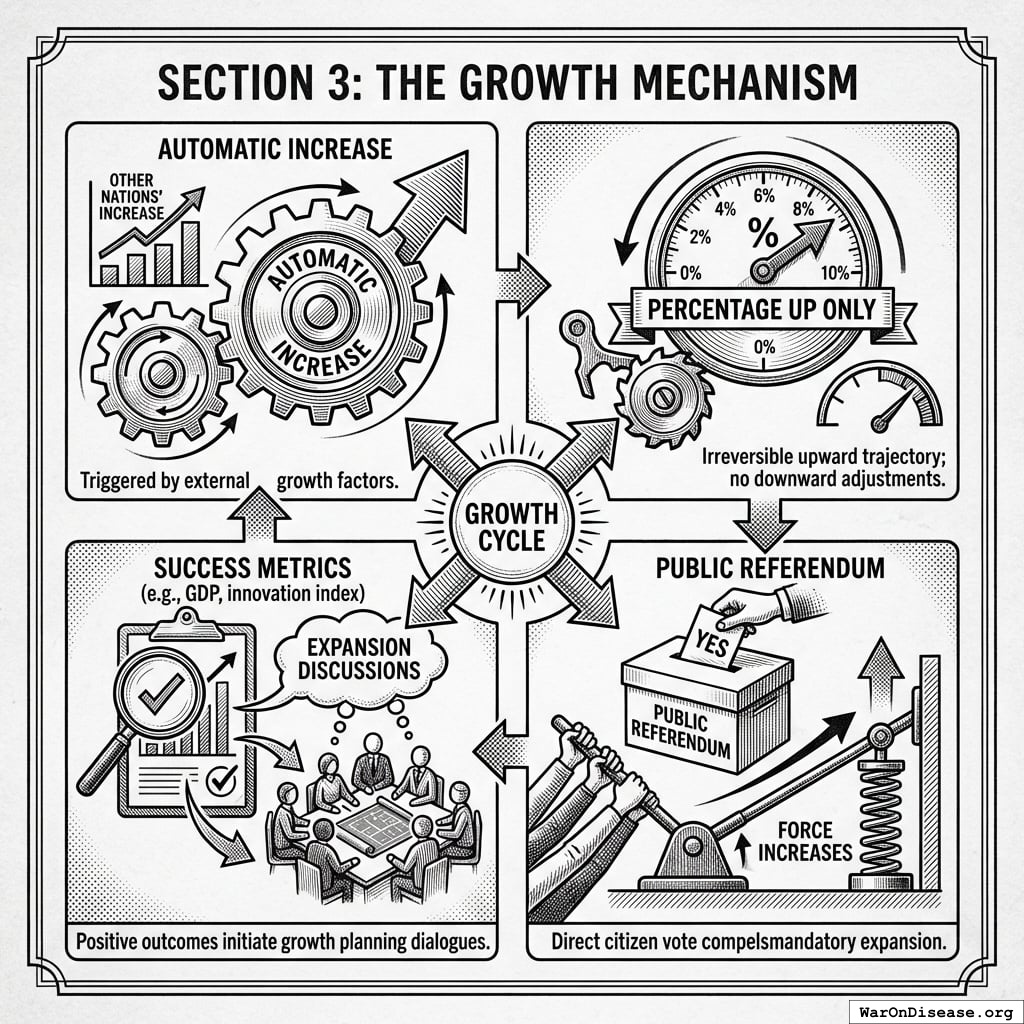
- Automatic increase if other nations increase
- Percentage can only go up, never down
- Success metrics trigger expansion discussions
- Public referendum can force increases
Making It Hard to Kill
The Constitutional Approach
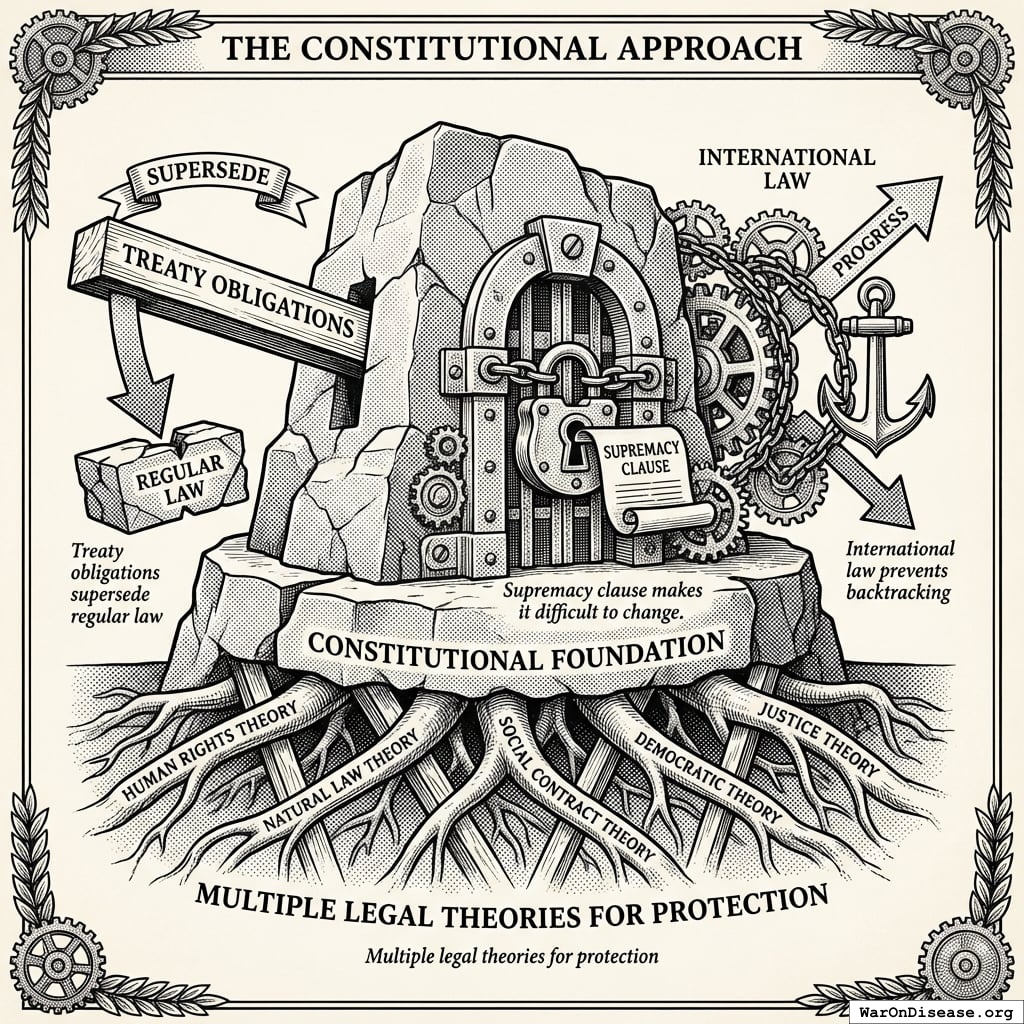
- Treaty obligations supersede regular law
- Supremacy clause makes it difficult to change
- International law prevents backtracking
- Multiple legal theories for protection
The Political Protection
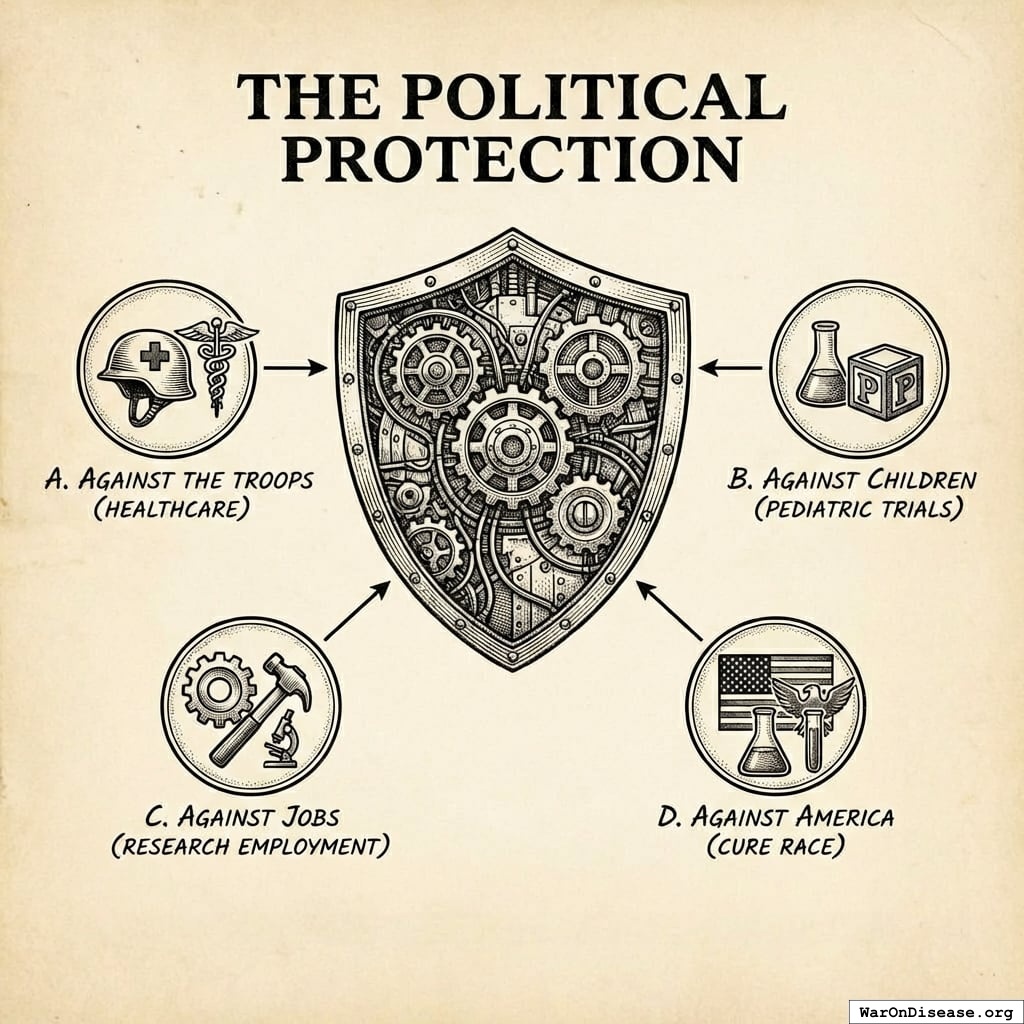
- Touching it means you’re “against the troops” (their healthcare)
- And “against children” (pediatric trials)
- And “against jobs” (research employment)
- And “against America” (America is winning the cure race)
The Technical Protection
- Smart contracts execute automatically
- Multiple backup execution methods
- International oversight and verification
- Blockchain immutability prevents tampering
The Incremental Implementation
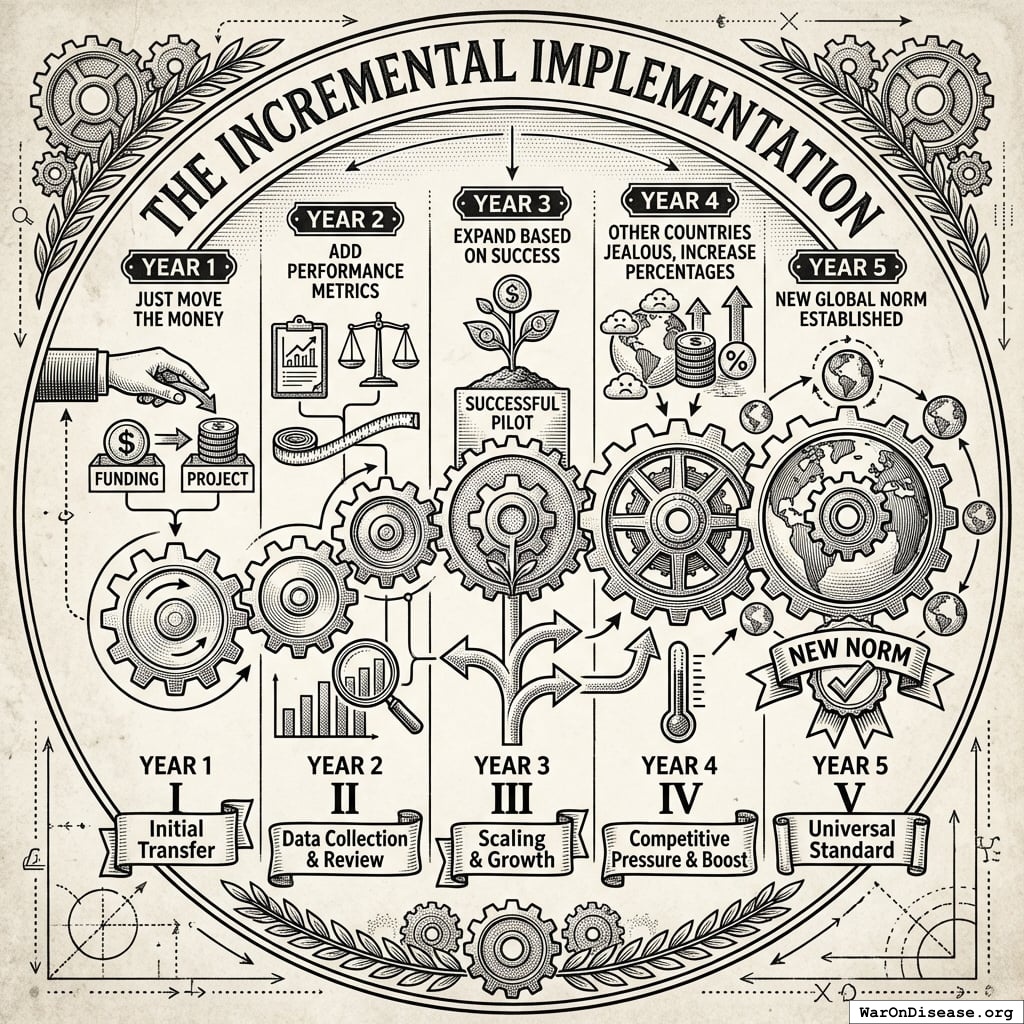
Year 1: Move the money. Fund 23.4 million patients/year (90% CI: 9.21 million patients/year-93.7 million patients/year) trial slots. Publish results. Year 2: First treatments reach patients. Politicians discover cured constituents vote. Year 3: Other countries notice their neighbors are getting healthier and richer. Increase to 2%. Year 5: The 1% Treaty is no longer controversial. It is a line item. Nobody remembers what the fuss was about, the same way nobody remembers opposing seatbelts.
The Legislative Strategy: Order of Operations
Here’s how you pass all five bills:
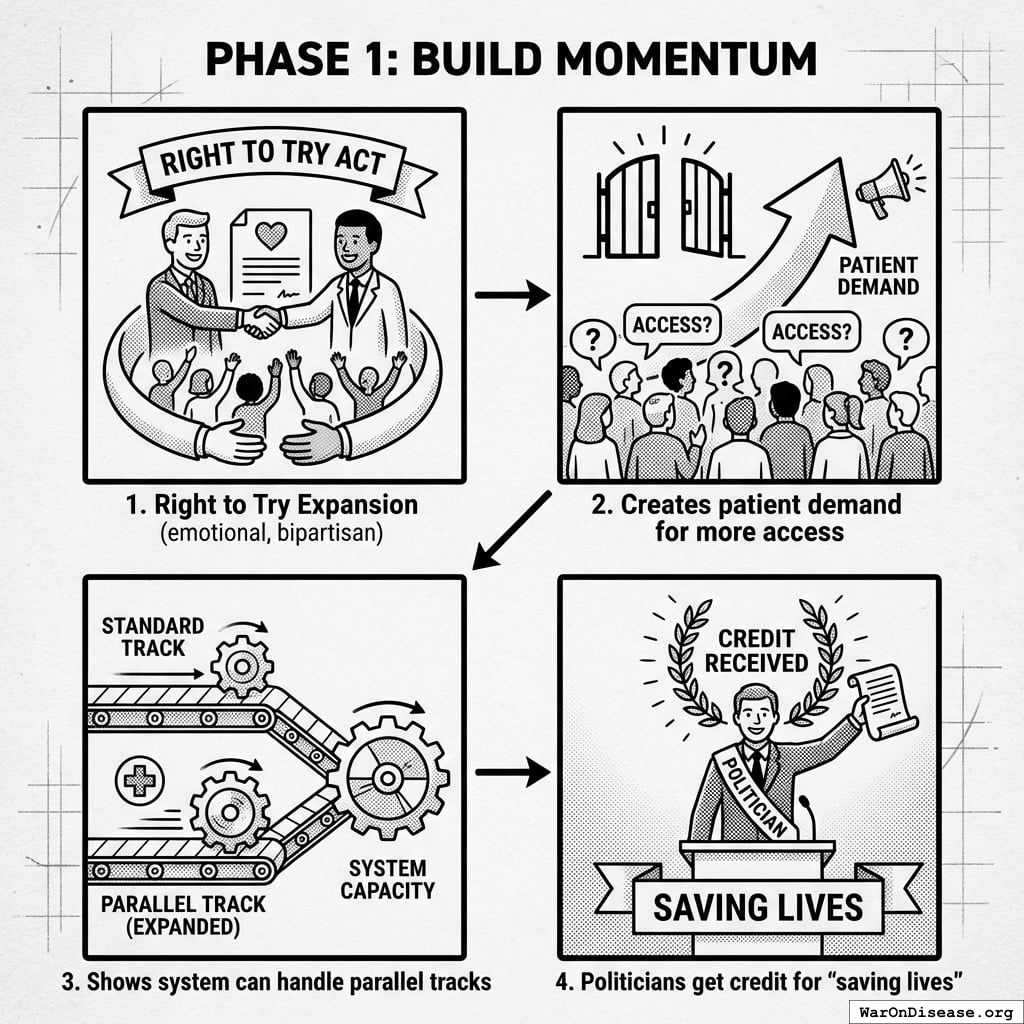
Phase 1: Build Momentum
- Right to Try Expansion goes first (emotional, bipartisan)
- Creates patient demand for more access
- Shows system can handle parallel tracks
- Politicians get credit for “saving lives”
Phase 2: Create Infrastructure
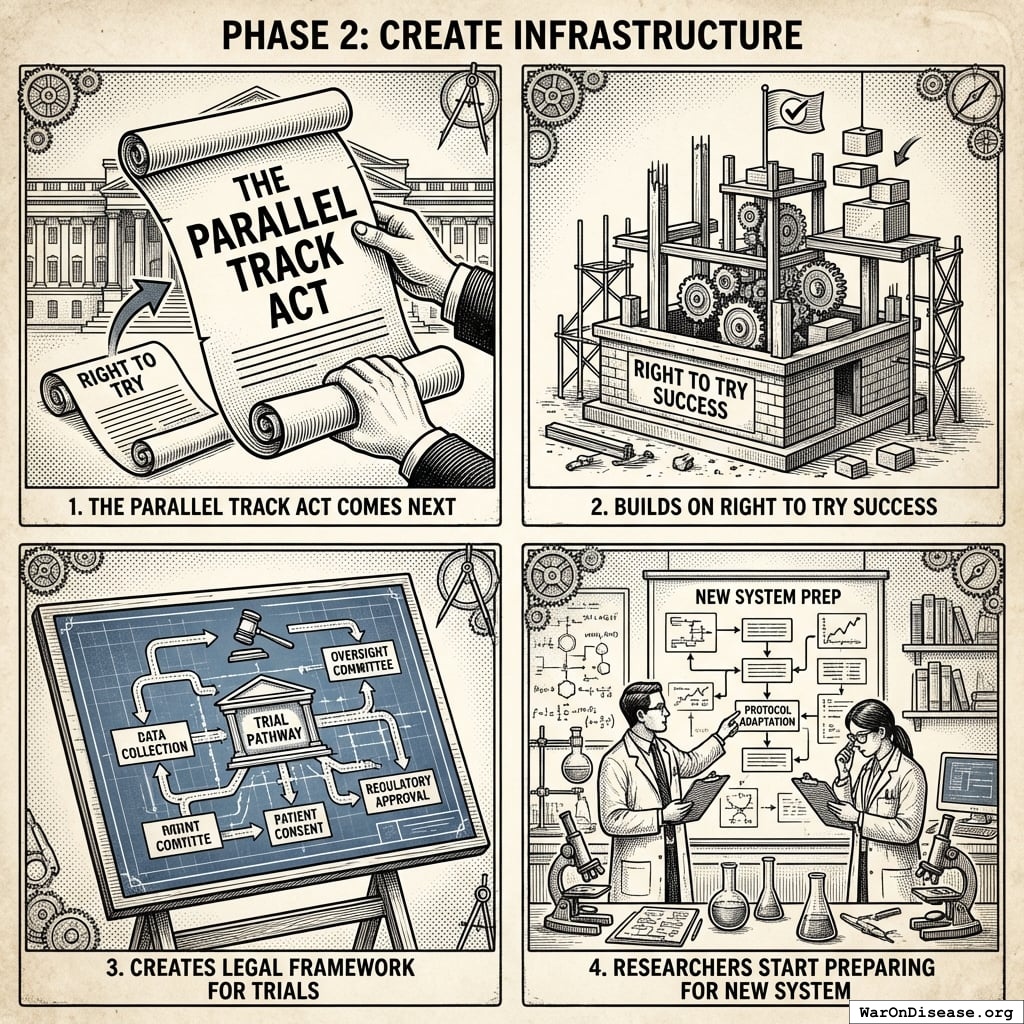
- The Parallel Track Act comes next
- Builds on Right to Try success
- Creates legal framework for trials
- Researchers start preparing for new system
Phase 3: Fund the System
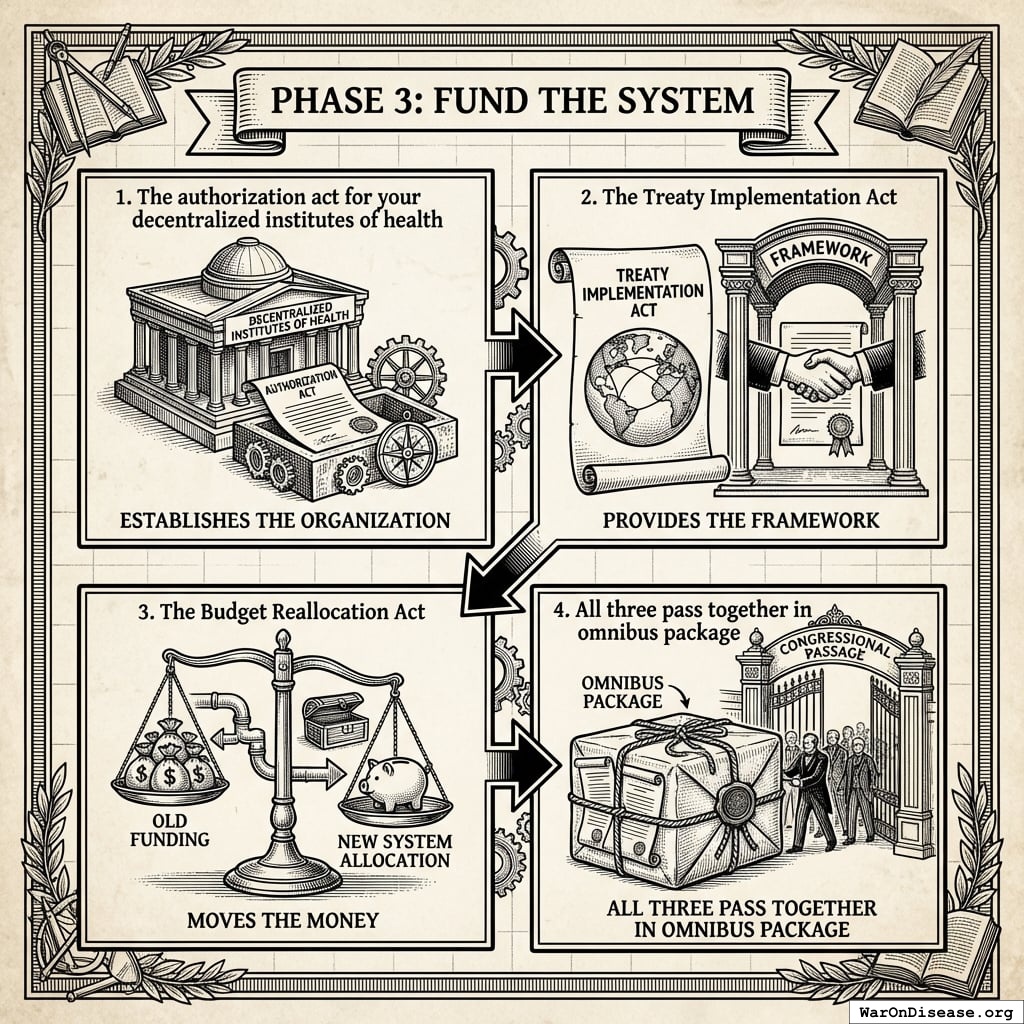
- The authorization act for your Decentralized Institutes of Health establishes the organization
- The Treaty Implementation Act provides the framework
- The Budget Reallocation Act moves the money
- All three pass together in omnibus package
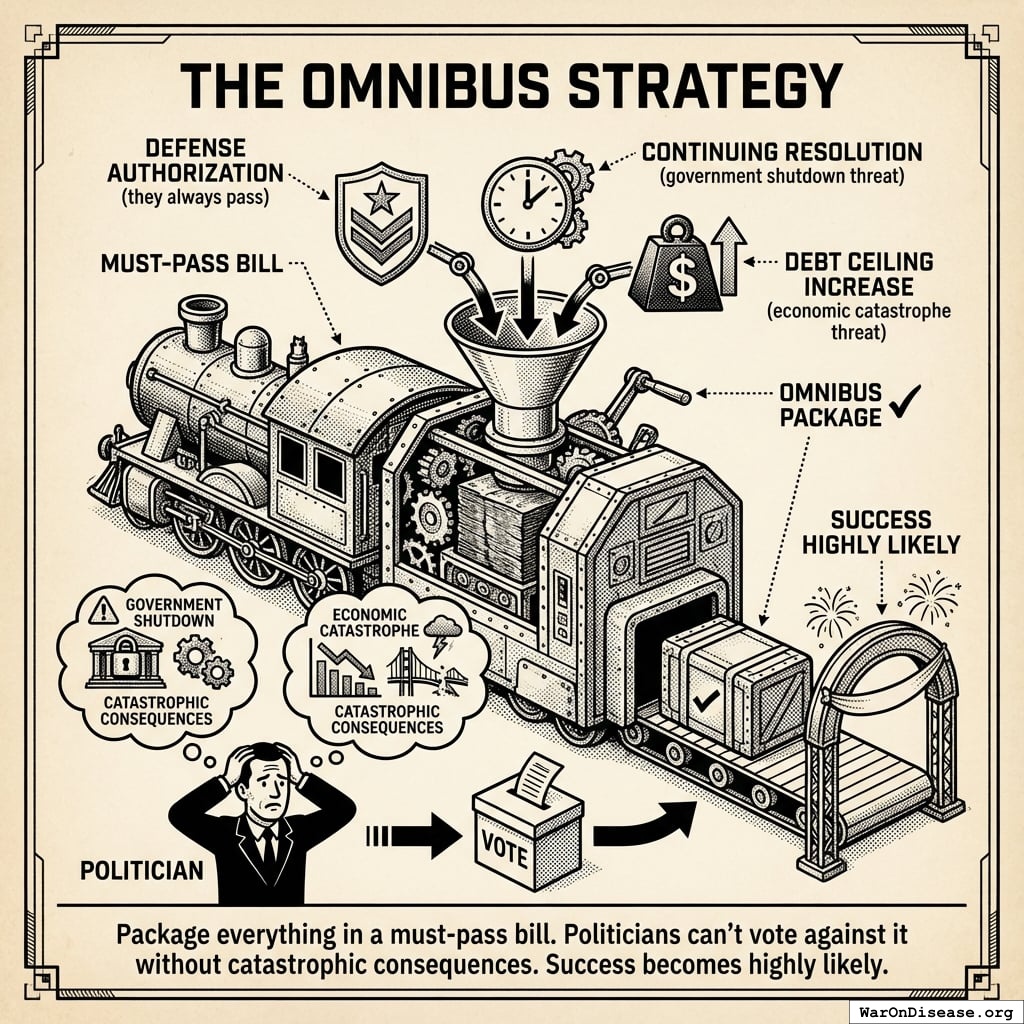
The Omnibus Strategy
Package everything in a must-pass bill:
- Military authorization (they always pass)
- Or continuing resolution (government shutdown threat)
- Or debt ceiling increase (economic catastrophe threat)
Politicians can’t vote against it without catastrophic consequences. Success becomes highly likely.
Conclusion: Democracy Theater at Its Finest
None of this changes how democracy works. That’s the point. Five bills that convert a system profiting from death into one profiting from life.
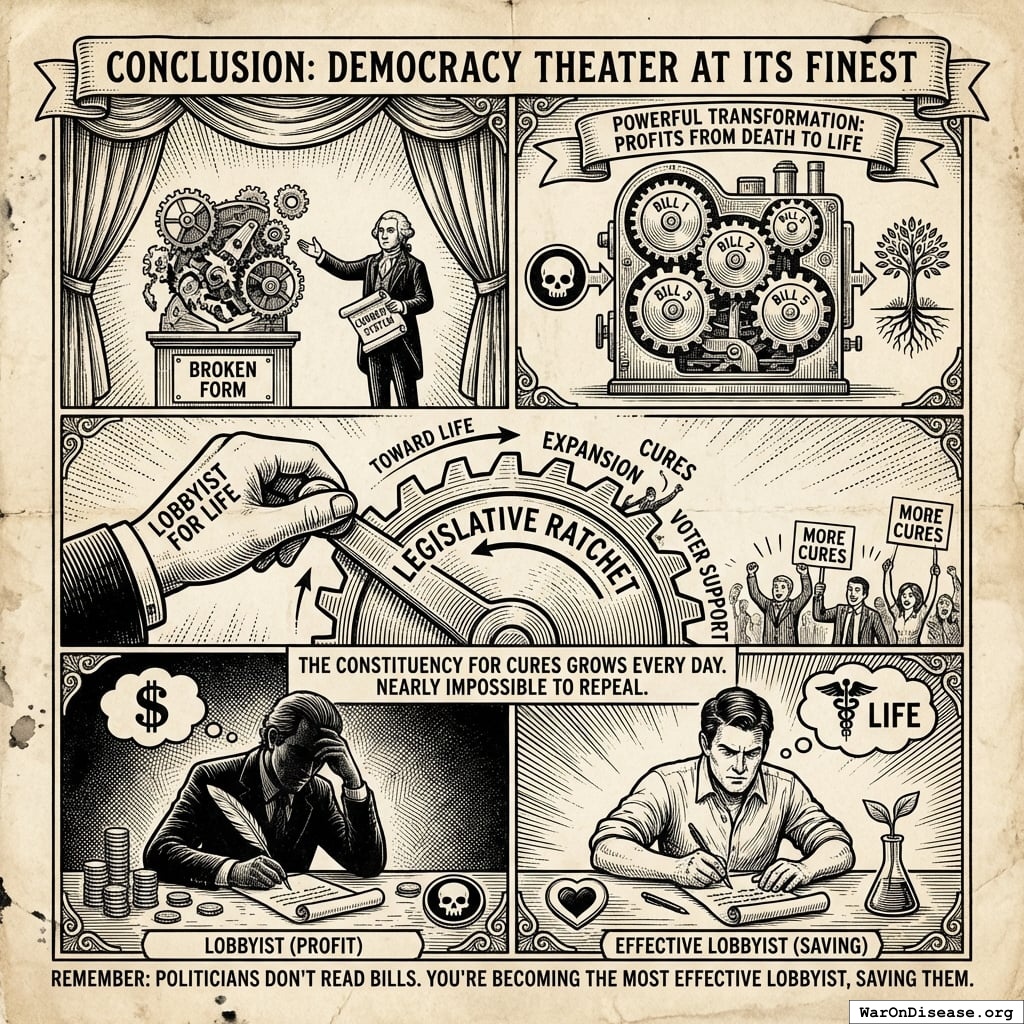
Once passed, they are nearly impossible to repeal. Every person treated becomes a voter for expansion. Every cure makes the next bill easier to pass. The ratchet only turns one direction.
Politicians do not read bills. Lobbyists write them. This is the lobbyist’s playbook, except the client is everyone and the product is not dying.